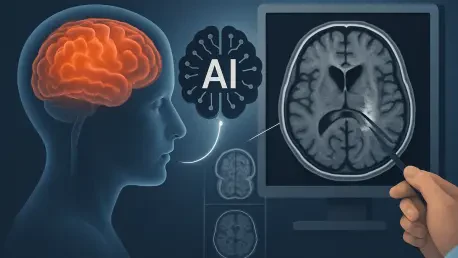

The superior performance of meta-learning architectures over standalone neural networks reflects a growing consensus that hybrid models are better suited for clinical applications. As of 2026, the global medical community is witnessing a sharp increase in the prevalence of Parkinson’s disease, a trend that is projected to continue through 2030 and beyond. This neurodegenerative condition is primarily characterized by the progressive loss of dopamine-producing neurons within the brain, leading to a debilitating array of motor symptoms such as tremors, rigidity, and bradykinesia, alongside non-motor complications like cognitive decline and mood disorders. Despite the rising patient numbers, early diagnosis remains notoriously difficult because the initial signs of the disease often overlap with common age-related changes or other neurological conditions. Consequently, there is an urgent need for objective, non-invasive diagnostic tools that can identify the disease at its inception. Recent breakthroughs in artificial intelligence, specifically in the fields of computer vision and deep learning, offer a promising solution by enabling the detection of subtle structural biomarkers in magnetic resonance imaging (MRI) scans that are frequently invisible to the human eye during a standard radiological review.
Standardizing Data and Preparing Images
The integrity of any diagnostic artificial intelligence system depends heavily on the quality and diversity of the data used during its development phase. In this recent study, researchers utilized a comprehensive dataset consisting of 3,114 T1-weighted MRI scans obtained from the Parkinson’s Progression Markers Initiative (PPMI), a premier international repository for neuroimaging. To ensure the model was robust and free from algorithmic bias, the investigators meticulously balanced the dataset, including 1,575 scans from confirmed Parkinson’s patients and 1,539 scans from healthy control subjects. This equilibrium is crucial in clinical machine learning because it prevents the software from developing a statistical preference for one diagnosis over another, which is a common pitfall in medical datasets that are often skewed toward healthy populations. By using such a large and standardized cohort, the study provides a high level of confidence that the identified patterns are representative of the actual pathology rather than coincidental findings within a small or biased sample group.
Beyond the initial data acquisition, the raw MRI scans required a sophisticated multi-stage preprocessing pipeline to ensure that the neural network could analyze the images effectively. Structural brain imaging is inherently prone to noise and variability caused by different scanner hardware, magnetic field inhomogeneities, and slight variations in patient positioning. To address these issues, the research team employed a series of technical corrections, including spatial denoising and N4 bias-field correction, which levels out low-frequency intensity variations across the image. Furthermore, the scans underwent min-max intensity normalization and were registered to the MNIPD25 brain template to ensure anatomical alignment across all subjects. Because the core architecture of the InceptionV3 model is designed for two-dimensional inputs, the researchers extracted median anatomical slices and resized them to a standard 299×299 pixel resolution. This rigorous preparation process effectively transformed raw, heterogeneous medical data into a clean, standardized format that highlights relevant neuroanatomical features while discarding irrelevant environmental artifacts.
Leveraging Deep Learning for Feature Extraction
The technological core of this diagnostic framework is the InceptionV3 architecture, a deep convolutional neural network that has been adapted through a process known as transfer learning. Originally designed for general image recognition tasks, InceptionV3 is particularly powerful because it utilizes parallel filter banks that can capture features at various spatial scales simultaneously. By “unfreezing” the top 30 layers of a pretrained version of this network and fine-tuning it with specific brain scans from the PPMI dataset, the researchers were able to train the model to recognize the unique neuroanatomical signatures of Parkinsonian decay. This approach allows the system to leverage preexisting knowledge of shapes and textures while specializing in the subtle changes in brain density and structure that characterize neurodegeneration. During the fine-tuning phase, the model achieved a validation accuracy of 93.9%, demonstrating its ability to distinguish between diseased and healthy brain tissue with high reliability before even reaching the final classification stage.
Following the fine-tuning process, the InceptionV3 model served as a high-dimensional feature extractor, effectively converting each complex brain image into a dense vector of 2,048 deep descriptors. These descriptors function as a digital fingerprint, representing a distilled summary of the structural integrity of the brain’s midbrain and subcortical regions. This vectorization process is vital because it moves the diagnostic task away from raw pixel analysis toward a more conceptual understanding of the patient’s anatomy. These high-level features capture complex relationships between different brain structures, such as the specific patterns of atrophy that occur as dopamine-producing neurons are lost. By translating visual information into a mathematical format, the framework provides the necessary groundwork for advanced machine learning classifiers to make highly accurate predictions about a patient’s clinical status. This stage bridges the gap between raw neuroimaging and actionable medical data, providing a level of detail that surpasses conventional diagnostic methods.
Optimizing Classification With Stacking Ensembles
The primary innovation of this diagnostic framework lies in its rejection of the single-model approach in favor of a “stacking ensemble” architecture. In this system, the 2,048 deep features extracted by the InceptionV3 model are fed into multiple “base learners” working in parallel, including Support Vector Machines (SVM) and two distinct configurations of Multilayer Perceptrons (MLP). Each of these algorithms has a different mathematical approach to identifying patterns; for instance, the SVM uses a radial basis function to find the optimal boundary between classes, while the MLPs use layers of artificial neurons to model nonlinear relationships. By processing the data through multiple lenses simultaneously, the ensemble system can capture a broader spectrum of diagnostic signals than any individual model could on its own. This diversity in the decision-making process is essential for medical applications where the biological presentation of a disease can vary significantly from one patient to another.
The final layer of the ensemble is a “meta-classifier” that uses logistic regression to synthesize individual predictions from the base learners into a single, authoritative diagnosis. This meta-learning approach effectively learns which underlying model is most reliable for specific types of data, allowing it to correct for individual errors and produce a more stable overall output. The results of this methodology were exceptional, with the ensemble achieving a peak diagnostic accuracy of 98.4% and an Area Under the Curve (AUC) of 0.999. In practical terms, this means the system misclassified only 50 images out of more than 3,100, a significant improvement over the performance of standalone models like the SVM, which only reached 79.8% accuracy. This high precision, combined with a strong recall rate of 0.987, suggests that the system is not only highly accurate but also extremely effective at avoiding false negatives, ensuring that patients with the disease are not overlooked during the screening process.
Ensuring Transparency and Clinical Validity
One of the most significant barriers to the adoption of artificial intelligence in healthcare is the “black box” problem, where clinicians are unable to see the reasoning behind a computer’s decision. To address this, the research team integrated explainable AI (XAI) tools, such as Gradient-weighted Class Activation Mapping (Grad-CAM) and Local Interpretable Model-agnostic Explanations (LIME). These tools generate visual heatmaps that highlight the specific regions of the brain scan that influenced the model’s prediction. The analysis confirmed that the AI focused its attention on the midbrain and other subcortical structures known to be affected by Parkinson’s pathology, rather than irrelevant factors like the margins of the scan or noise from the imaging hardware. This level of transparency is vital for building trust within the clinical community, as it allows radiologists to verify that the software is basing its diagnosis on medically relevant biological markers.
The inclusion of rigorous ablation studies further validated the importance of each component in the system’s pipeline. For example, researchers found that removing feature scaling or simplifying the meta-classifier to a basic voting mechanism significantly reduced the overall accuracy of the system. These findings emphasized that the high performance of the framework was a result of the careful synergy between image preprocessing, deep feature extraction, and ensemble learning. Furthermore, the use of a 5-fold cross-validation scheme ensured that the results were not the product of overfitting to a specific subset of data. By partitioning the data at the patient level, the investigators guaranteed that the model was truly learning to recognize the disease rather than simply memorizing the specific characteristics of individual scans. This methodological rigor ensures that the system is well-positioned for future testing in broader, more diverse clinical environments where imaging conditions may vary.
Future Directions for Automated Clinical Diagnostics
The successful implementation of this hybrid AI framework provides a clear roadmap for the evolution of neurological diagnostics through 2028. While current results are based on 2D slices for computational efficiency, moving toward 3D convolutional neural networks is a critical next step. Processing the entire volumetric context of the brain would likely uncover even more subtle structural biomarkers, particularly those related to the connectivity between different brain regions. Additionally, the study highlighted the importance of validating these models against “real-world” data from local clinics where MRI hardware might not be as advanced as the machines used in the PPMI study. Ensuring that the algorithm maintains its 98.4% accuracy across various magnetic field strengths, such as 1.5T and 3.0T scanners, is a high priority for the next phase of development.
The integration of such high-precision AI tools into standard radiological workflows would mark a transformative shift for the management of Parkinson’s disease. By providing clinicians with an objective second opinion, these systems could facilitate earlier interventions, which are proven to significantly improve patient outcomes and quality of life. The researchers concluded that the combination of InceptionV3 and stacking ensembles represents a state-of-the-art approach to neuroimaging analysis, offering a level of reliability that could eventually support universal screening programs. Future efforts are directed toward multimodal analysis, where MRI data would be combined with genetic markers and wearable sensor data to create an even more comprehensive diagnostic profile. Ultimately, the research demonstrated that the marriage of meta-learning and deep computer vision provides a robust solution to one of the most persistent challenges in modern neurology.